
The landscape of personal health tracking has shifted from reactive clinical visits to proactive, continuous monitoring. At the center of this evolution is the management of hypertension—a condition affecting over a billion people worldwide. For decades, the standard upper-arm inflatable cuff has reigned supreme in both clinics and homes. However, the rise of sleek, sensor-packed smartwatches claiming to measure blood pressure directly from the wrist has introduced a major shift in how consumers track their cardiovascular health.

While the convenience of a wrist-worn tracker is undeniable, it forces a critical evaluation of clinical efficacy versus consumer accessibility. To make informed decisions about your health, it is essential to look closely at the mechanics, emerging challenges, and specific technological gaps between wrist-based blood pressure watches and traditional upper-arm cuff monitors.
1. Technological Architecture: How They Measure Pressure
The fundamental difference between these two categories lies in their underlying methodology. One relies on mechanical physics, while the other relies on optical and mathematical estimation.
The Upper-Arm Cuff: Oscillometric Measurement
Traditional automated cuff monitors utilize the oscillometric method. When the cuff inflates around the upper arm, it temporarily cuts off blood flow through the brachial artery. As the cuff slowly deflates, the monitor detects the oscillations (vibrations) of the arterial wall caused by the pulsing blood.
- Systolic Pressure is determined when the blood first begins to force its way back through the compressing artery.
- Diastolic Pressure is measured when the cuff pressure drops below the artery’s resting pressure, and blood flows smoothly without causing vibrations.
Because it acts directly on a major artery located close to the heart, the upper-arm cuff interacts with the actual physical forces of your circulatory system.
The Smartwatch: Optical Photoplethysmography (PPG) and Mathematical Modeling
With rare exceptions, a smartwatch does not possess an inflatable bladder. Instead, it relies on Photoplethysmography (PPG). Optical sensors shine light into the microvasculature (tiny blood vessels) of the wrist, measuring how much light is absorbed by the blood flow with every beat.
The device captures a pulse waveform, and proprietary AI algorithms analyze variables such as wave velocity, shape, and amplitude. The watch then applies a mathematical formula to estimate what the corresponding blood pressure in the main arteries should be. It is an indirect inference, not a direct physical measurement.
2. Head-to-Head Comparison: Operational Realities
| Feature | Traditional Upper-Arm Cuff | Smartwatch BP Monitor |
| Measurement Type | Direct physical forces (Oscillometric) | Indirect proxy estimation (Optical PPG) |
| Artery Targeted | Brachial Artery (Large, close to heart) | Radial/Ulnar Arteries & Capillaries (Small, peripheral) |
| User Convenience | Low (Bulky, requires sitting still, manual setup) | High (Continuous, passive, seamless) |
| Calibration Requirement | None (Requires factory calibration every few years) | High (Often requires monthly anchoring with a cuff) |
| Clinical Acceptance | Universal gold standard for home tracking | Skeptical; used primarily for lifestyle trends |
3. Emerging Technical Challenges for Wearable BP Technology
As wearable tech attempts to move from a novelty feature to a legitimate diagnostic tool, developers are confronting severe physiological and technological bottlenecks.
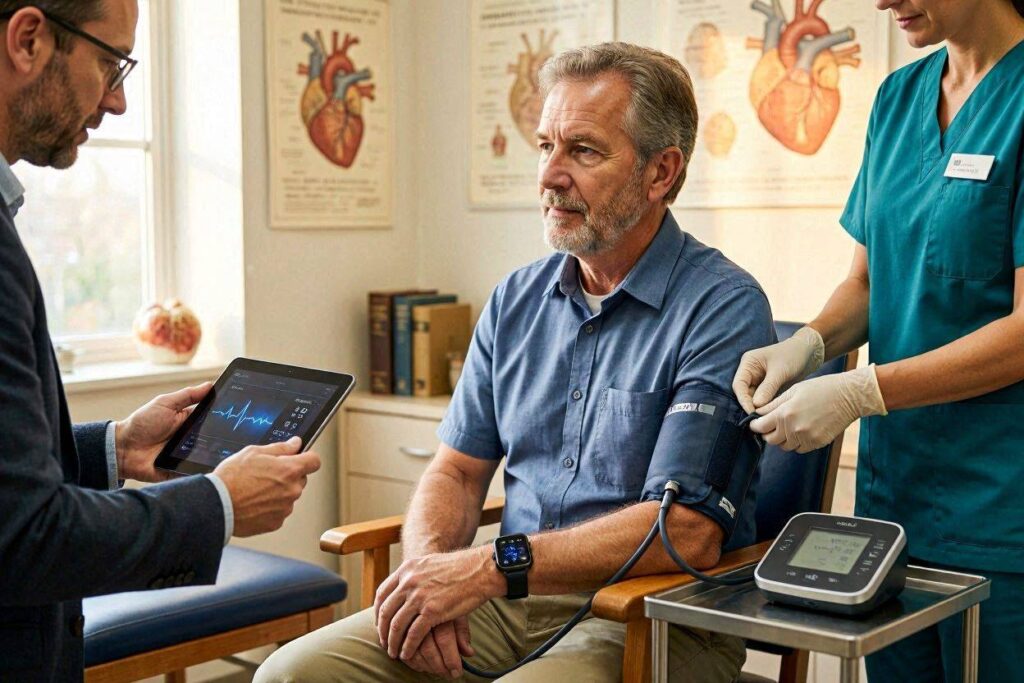
The Peripheral Dissociation Phenomenon
Blood pressure is not uniform throughout the body. As blood travels from the aorta down to the tiny vessels in the wrist, the shape of the pulse pressure wave changes due to arterial branching and reflections. This is known as pulse pressure amplification.
During periods of stress, temperature changes, or exercise, the blood vessels in the wrist may constrict or dilate independently of the main arteries in the arm. A smartwatch reading the wrist can register a completely different physiological state than an upper-arm cuff, leading to mismatched data that frustrates both patients and doctors.
The Hidden Trap of Algorithmic “Smoothing”
Because optical sensors are highly sensitive to movement, raw smartwatch data is incredibly noisy. To present a readable number to the user, the watch’s software utilizes aggressive data smoothing.
If a patient experiences an acute, dangerous hypertensive crisis (a sudden spike in blood pressure), the watch’s algorithm may treat this sudden variance as anomalous “noise” or lean too heavily on the user’s historical baseline data. Consequently, the watch may output a falsely normalized reading, failing to alert the user to a genuine medical emergency.
Skin Pigmentation and Signal Attenuation
A major equity issue in optical sensor design is the impact of melanin on light absorption. Darker skin tones naturally absorb more green light (the wavelength most commonly used in PPG sensors). If the software algorithm does not dynamically adjust its sensor intensity and mathematical scaling for varying skin tones, the accuracy of the pulse wave capture degrades significantly, resulting in higher error rates for diverse populations.
4. Operational Challenges of the Traditional Cuff
While the traditional cuff is far more accurate, it is not without its flaws. The challenges associated with cuffs are primarily centered around user error and compliance:
- The Sizing Dilemma: Using a cuff that is too small for the arm circumference falsely elevates blood pressure readings, while a cuff that is too large underreports it. Many household users do not properly measure their arms before buying a device.
- White-Coat and Masked Hypertension: The physical act of putting on a tight, loud, inflating cuff can induce anxiety in certain individuals, artificially raising their blood pressure during the test itself (White-Coat Effect).
- Poor Compliance: Because taking a cuff reading requires stopping all activity, sitting quietly for five minutes, and keeping the arm elevated at heart level, users rarely take readings frequently enough to capture a true picture of their daily blood pressure variations.
5. Clinical Implications: The Danger of Mismanaged Expectations
The core risk of the watch-versus-cuff debate is the potential for patient self-mismanagement.
If a smartwatch regularly underreports blood pressure due to a faulty calibration baseline, a patient might assume their hypertension is under control and skip their prescribed medication. Conversely, if a watch overcorrects for motion artifacts and displays a highly elevated reading, it can induce health panic, driving unnecessary emergency room visits and straining medical infrastructure.
Medical consensus remains clear: consumer smartwatches are not diagnostic replacements. They function effectively as early-warning lifestyle indicators. If a watch flags a consistent change in blood pressure trends over several weeks, that trend should always be verified using a clinically validated oscillometric upper-arm cuff before any medical choices are made.
6. Closing the Accuracy Gap
To bridge the divide between the convenience of the watch and the precision of the cuff, the medical tech industry is moving away from basic optical guessing toward more robust, multi-layered tracking methodologies.
Engineers are currently testing bioimpedance sensors—which pass microscopic electrical currents through the wrist to measure changes in tissue fluid—and pairing them with optical data to get a clearer picture of arterial wall movement. Additionally, some manufacturers are miniaturizing physical inflation mechanisms, building micro-bladders directly into heavy-duty smartwatch bands to provide true oscillometric tracking on the go.
Until these advanced hybrid sensors become standard, the upper-arm cuff remains the anchor of cardiovascular safety, while the smartwatch serves as a useful, though imperfect, companion.

